All published articles of this journal are available on ScienceDirect.

Work-Life Balance and Leisure Engagement in Relation to Burnout among Nurses: A Comparative Study of Public and Private Hospitals
 Datin Hafizah Che Hassan2
Gundluru Aruna1
Assyifa Antomy Putri1
Authors Info & Affiliations
Abstract
Background
Burnout among nurses continues to be a major concern, with implications for patient safety, quality of care, and workforce stability. Work-Life Balance (WLB) and engagement in leisure activities are often considered protective factors. However, limited research has explored whether WLB influences how leisure activities contribute to reducing burnout, particularly across different hospital sectors. This study aimed to investigate the moderating role of WLB in the relationship between leisure activity engagement and burnout among nurses, and to compare these relationships between public and private hospitals.
Methods
A cross-sectional study was conducted involving 168 nurses working in public and private hospitals in Riau, Indonesia. Burnout was assessed using the Maslach Burnout Inventory-Human Services Survey, WLB was measured with a validated scale, and leisure engagement was evaluated using a structured index. Multivariable linear regression with interaction terms was applied, controlling for demographic and occupational factors. Subgroup analyses were conducted based on hospital type.
Results
Nurses in private hospitals reported higher levels of burnout and poorer WLB compared to those in public hospitals. Leisure engagement was associated with lower burnout only among nurses with adequate WLB. The moderating effect of WLB was significant in both groups, with a stronger effect observed in private hospitals. Shift work, extended working hours, and high workload were consistently associated with increased burnout.
Conclusion
WLB plays a critical moderating role in strengthening the protective effect of leisure activities on burnout. Integrating WLB-supportive policies with opportunities for restorative leisure may be essential for improving nurse well-being and maintaining quality care.
1. INTRODUCTION
Burnout among nurses has increasingly been recognized as a serious issue affecting both the healthcare workforce and patient safety worldwide. This condition is typically reflected in emotional exhaustion, a sense of detachment from patients, and a decline in professional effectiveness, often resulting from prolonged exposure to workplace stress. A growing body of evidence indicates that burnout among nurses is linked to compromised patient safety, reduced quality of care, and lower levels of patient satisfaction, emphasizing that its impact extends beyond individual well-being to organizational outcomes [1, 2]. In the period following the COVID-19 pandemic, the risk of burnout has become even more pronounced, with nurses reporting higher levels of burnout and lower job satisfaction compared to other healthcare professionals [3]. These patterns highlight the urgent need for effective management strategies that not only address occupational stress but also ensure long-term workforce sustainability.
One of the key factors influencing nurses’ well-being is Work-Life Balance (WLB), which refers to an individual’s ability to manage professional responsibilities alongside personal and family roles. In nursing contexts, achieving WLB is often challenging due to demanding work conditions, including rotating shifts, extended working hours, high patient acuity, and ongoing staffing shortages. Previous research has shown that nurses who experience better WLB tend to report higher levels of work engagement and improved psychological well-being [4]. In contrast, poor balance between work and personal life has been associated with negative outcomes such as emotional distress, dissatisfaction, and conflict between work and family roles [5, 6]. Additionally, a recent scoping review suggests that WLB among hospital nurses is shaped by multiple interacting factors, ranging from individual characteristics to organizational policies and broader health system influences [7]. Taken together, these findings suggest that WLB functions as an important resource within the nursing work environment.
In addition to workplace conditions, there has been growing interest in leisure-based activities as a means of promoting recovery from work-related stress among nurses. Leisure activities, which include voluntary and enjoyable pursuits outside of work, can support psychological detachment, relaxation, skill development, and social interaction. These processes are essential for restoring mental and emotional energy after demanding work shifts. Empirical studies have demonstrated that structured leisure programs can help reduce stress, anxiety, and depressive symptoms among nurses [8]. Furthermore, observational research indicates that higher levels of physical activity are associated with lower burnout, partly through improved recovery experiences [9]. Recent studies have also highlighted the concept of “leisure crafting,” in which individuals intentionally shape their leisure time to enhance meaning and satisfaction, as an important predictor of burnout outcomes using advanced analytical approaches. Overall, these findings suggest that leisure engagement represents a potentially modifiable behavioral strategy to mitigate burnout.
However, the benefits of engaging in leisure activities may not be experienced equally by all nurses. The extent to which leisure contributes to recovery may depend on an individual’s work-life balance. When WLB is poor, factors such as limited time, fatigue, and competing role demands may reduce the effectiveness of leisure activities as a recovery mechanism. On the other hand, nurses who maintain a healthier balance between work and personal life are more likely to fully benefit from leisure as a source of stress relief. Despite this theoretical assumption, many previous studies have treated WLB and leisure engagement as separate predictors of burnout, rather than examining whether WLB influences the strength of the relationship between leisure activities and burnout [4, 6, 9]. Consequently, there is still limited empirical evidence on how WLB shapes the protective effects of leisure engagement.
The organizational setting in which nurses work may further influence these relationships. Public and private hospitals often differ in terms of staffing arrangements, workload distribution, employment conditions, performance expectations, and available resources. Comparative studies have reported differences in burnout levels between these sectors, with nurses in private hospitals in Indonesia showing higher levels of emotional exhaustion and depersonalization. Similar patterns have been observed in other contexts, such as Nigeria, where variations in working conditions and work-life experiences were found between nurses in public and private healthcare facilities [10]. These findings suggest that institutional context may play an important role in shaping both WLB and burnout, as well as the effectiveness of coping strategies such as leisure engagement.
For this reason, hospital type was considered a potential moderating factor in the present study. Differences in organizational structure, workload demands, employment arrangements, and support systems between public and private hospitals may influence how nurses experience work-life balance, engage in leisure activities, and ultimately develop burnout [11]. Previous research has also indicated that key factors such as rotating shift work, which is strongly associated with burnout, may be implemented differently across hospital settings [12]. Drawing on theoretical frameworks such as the Job Demands-Resources model and Conservation of Resources theory, it can be argued that the organizational environment plays a critical role in determining how personal resources, including leisure activities, contribute to stress reduction. Therefore, hospital type represents a meaningful contextual variable in understanding burnout dynamics.
In addition, job-related factors such as shift work and workload intensity would further complicate these relationships. A recent systematic review has confirmed that rotating shift work is a significant contributor to burnout among nurses and highlights the need for organizational interventions to address this issue [12]. Evidence from cross-sectional studies, including research conducted in Malaysia, also shows that nurses working shifts experience considerable levels of burnout. Since work schedules, staffing levels, and job demands often vary between public and private hospitals, it is reasonable to expect that the relationships between leisure engagement, WLB, and burnout may differ across these contexts.
Although previous studies have established links between burnout, work-life balance, and recovery-related behaviors, several important gaps remain. Many studies have focused on examining WLB and leisure engagement as independent factors, without considering the possibility that WLB may act as a moderator influencing the relationship between leisure engagement and burnout [4, 9]. In addition, relatively few studies have compared these dynamics across public and private hospital settings, despite clear evidence of differences in working conditions and burnout levels between these sectors [10, 11]. Furthermore, not all studies have adequately controlled for important occupational variables such as shift work, unit type, working hours, tenure, and workload, which are known to influence burnout risk [12]. Without accounting for these factors, it is difficult to fully understand the context-specific roles of WLB and leisure engagement.
Therefore, this study aims to investigate whether work-life balance moderates the relationship between leisure-based activity engagement and burnout among nurses. It also seeks to compare these relationships between public and private hospitals while controlling for relevant demographic and occupational variables, including age, gender, marital status, unit type, shift work, working hours, tenure, and workload. By examining these interactions, the study aims to provide practical insights for healthcare managers and policymakers in developing more targeted and effective strategies to improve nurse well-being and reduce burnout.
2. METHODS
2.1. Study Design
This study adopted an analytical cross-sectional observational design to explore the relationship between leisure-based activity engagement and burnout among nurses. In addition, it examined whether Work-Life Balance (WLB) acts as a moderating factor in this relationship. Hospital type (public vs. private) was also considered as a contextual factor and included in subgroup comparisons. The reporting of this study followed the STROBE (Strengthening the Reporting of Observational Studies in Epidemiology) guidelines to ensure clarity and transparency.
2.2. Setting
Data collection was conducted at four hospitals located in Riau Province, Indonesia, comprising two public and two private hospitals. The participating hospitals were selected purposively based on their comparable service characteristics, availability of inpatient and critical care facilities, and willingness to participate in the study. These hospitals represented different organizational structures and management systems, enabling comparisons between the public and private healthcare sectors. Data were collected between November and December 2025 from nurses working in inpatient wards, Intensive Care Units (ICUs), and emergency departments, where occupational demands and exposure to burnout-related stressors are commonly observed.
2.3. Participants and Sample
Participants were eligible if they: (a) were registered nurses providing direct patient care, (b) had at least six months of working experience in their current hospital, (c) were aged 18 years or older, and (d) provided written informed consent.
Nurses were excluded if they: (a) were on extended leave during the data collection period (e.g., maternity or medical leave), (b) worked exclusively in administrative roles without direct patient contact, or (c) submitted questionnaires with more than 20% missing data on key variables.
The minimum sample size was estimated using G*Power 3.1 for multiple linear regression (fixed model; R2 deviation from zero). Assuming a medium effect size (f2 = 0.15), a significance level of 0.05, statistical power of 0.80, and 12 predictors, at least 127 participants were required. To account for potential non-response and to support subgroup analyses by hospital type, the target sample size was increased to a minimum of 160 nurses.
A stratified convenience sampling method was applied. Nursing units (e.g., ICU, emergency, and general wards) were treated as strata within each hospital. Participants were recruited proportionally based on staff availability and shift schedules. This approach is commonly used in hospital-based research where random sampling is often difficult due to clinical workload and rotating shifts.
2.4. Measures
Burnout was measured using the Maslach Burnout Inventory-Human Services Survey (MBI-HSS), a 22-item instrument that assesses three dimensions: emotional exhaustion, depersonalization, and personal accomplishment. Responses are rated on a 7-point Likert scale ranging from 0 (“never”) to 6 (“every day”). Higher scores on emotional exhaustion and depersonalization indicate higher burnout, while lower scores on personal accomplishment reflect reduced professional efficacy. The MBI-HSS has been widely validated across healthcare settings and is considered a gold standard for burnout assessment [13]. The Indonesian version has demonstrated good reliability, with Cronbach’s alpha values of .90, .78, and .72 for the respective subscales [11]. In this study, internal consistency was further assessed using both Cronbach’s alpha and McDonald’s omega.
Work-life balance was assessed using the 15-item Work-Life Balance Scale, which captures three domains: work interference with personal life, personal life interference with work, and work-personal life enhancement [14]. Items are rated on a Likert scale, with higher scores Items are rated on a Likert scale, and negatively worded items were reverse-coded so that higher scores reflect better balance. Previous studies have shown strong reliability of this scale in healthcare populations, including Southeast Asian samples (α = .89).
Leisure-based activity engagement was assessed using a structured questionnaire developed specifically for this study based on previous leisure and recovery literature. The questionnaire evaluated five domains of leisure activities: physical activities, social interactions, religious or spiritual activities, creative hobbies, and passive leisure activities during the previous four weeks.
For each activity domain, participants reported frequency (number of occasions per week) and average duration per occasion (minutes). Frequency and duration scores were standardized using z-score transformation to ensure comparability across domains. The Leisure Engagement Index (LEI) was calculated by averaging standardized frequency and duration scores across all activity domains, with equal weighting applied because no theoretical or empirical evidence supported assigning greater importance to any specific leisure domain.
Content validity was assessed through expert review involving nursing and occupational health researchers to evaluate relevance, clarity, and cultural appropriateness of each item. A pilot assessment was conducted before the main study to identify ambiguous items and improve questionnaire comprehension. Internal consistency reliability of the LEI was examined using Cronbach’s alpha and McDonald’s omega. Construct validity and dimensionality were evaluated using an Exploratory Factor Analysis (EFA) prior to composite score generation [15]. The instrument was reviewed by experts and pilot-tested to ensure clarity, relevance, and cultural appropriateness [16].
2.5. Covariates
Based on prior literature in nursing and occupational health, several covariates were included: age, gender, marital status, hospital type, unit type, shift work status, weekly working hours, years of experience, and perceived workload.
2.6. Data Collection Procedure
Permission to conduct the study was obtained from hospital administrators and nursing managers before recruitment. Participants received both written and verbal explanations about the study, including its voluntary nature, confidentiality, and their right to withdraw at any time without consequences. Written informed consent was obtained prior to participation.
Data were collected by trained research assistants during shift changes or staff meetings. Participants completed self-administered questionnaires either on paper or through a secure online platform. The process took approximately 15-20 minutes. Completed questionnaires were checked for completeness, and participants were asked to clarify missing responses when necessary.
2.7. Statistical Analysis
Data analysis was conducted using SPSS version 29, with statistical significance set at p < .05 (two-tailed). Descriptive statistics were used to summarize the data. Prior to hypothesis testing, assumptions such as normality, linearity, multicollinearity, and homoscedasticity were carefully examined.
All Variance Inflation Factor (VIF) values were below 5, indicating no multicollinearity concerns. Leisure engagement and WLB were mean-centered before generating interaction terms. Although slight heteroscedasticity was observed, robust standard errors were applied to ensure reliable estimates.
Reliability was assessed using Cronbach’s alpha and McDonald’s omega, with all scales exceeding the acceptable threshold of .70. Confirmatory Factor Analysis (CFA) was conducted using AMOS version XX (or R lavaan package) to evaluate construct validity. Model fit was assessed using Comparative Fit Index (CFI), Tucker-Lewis Index (TLI), Root Mean Square Error of Approximation (RMSEA), and Standardized Root Mean Square Residual (SRMR). Standardized factor loadings above 0.50 were considered acceptable. Measurement invariance testing confirmed that the scales functioned equivalently across public and private hospital groups.
Missing data were examined before analysis. When missing values exceeded 5%, Multiple Imputation using Chained Equations (MICE) was applied. Five imputed datasets were generated, including demographic variables, burnout scores, WLB scores, leisure engagement scores, and occupational covariates. Interaction terms between leisure engagement and WLB were calculated within each imputed dataset following passive imputation procedures to maintain statistical consistency. Sensitivity analyses comparing complete-case and imputed datasets demonstrated comparable estimates (Fig. 1).
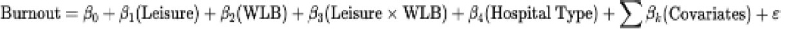
Multiple linear regression model with interaction effects on burnout.
The main hypothesis was tested using multivariable linear regression. An interaction term between leisure engagement and WLB was included to assess WLB’s moderating effect. Significant interactions were further explored using simple slope analysis at low (−1 SD), mean, and high (+1 SD) levels of WLB.
To examine differences by hospital type, interaction terms were tested, followed by stratified analyses for public and private hospitals. Results were reported as unstandardized coefficients (B), 95% Confidence Intervals (CIs), and p-values.
2.8. Ethical Considerations
This study received ethical approval from Universitas Hang Tuah (Approval No.: 008/KEPK/UHTP/XI/2025). Participation was voluntary, and all responses were anonymous and kept confidential. No personal identifiers were collected, and data were securely stored with access restricted to the research team.
3. RESULTS
A total of 168 nurses participated in this study, comprising 86 participants from public hospitals (51.2%) and 82 from private hospitals (48.8%). The average age of the sample was 31.6 ± 6.4 years. The majority were female (74.4%), married (62.5%), and engaged in rotating shift schedules (69.0%). In addition, more than half of the participants (57.7%) reported working over 40 hours per week (Table 1).
| Variable | Public (n = 86) | Private (n = 82) | Test | p-value |
|---|---|---|---|---|
| Age (years), mean ± SD | 32.1 ± 6.6 | 31.0 ± 6.2 | t = 1.09 | 0.28 |
| Gender | - | - | χ2 = 0.12 | 0.73 |
| Female | 65 (75.6%) | 60 (73.2%) | - | - |
| Male | 21 (24.4%) | 22 (26.8%) | - | - |
| Marital status | - | - | χ2 = 0.35 | 0.56 |
| Single | 31 (36.0%) | 32 (39.0%) | - | - |
| Married | 55 (64.0%) | 50 (61.0%) | - | - |
| Unit type | - | - | χ2 = 6.24 | 0.044* |
| Inpatient ward | 28 (32.6%) | 30 (36.6%) | - | - |
| ICU | 23 (26.7%) | 29 (35.4%) | - | - |
| Emergency | 35 (40.7%) | 23 (28.0%) | - | - |
| Rotating shift work | - | - | χ2 = 4.61 | 0.032* |
| Yes | 66 (76.7%) | 50 (61.0%) | - | - |
| No | 20 (23.3%) | 32 (39.0%) | - | - |
| Weekly working hours | - | - | χ2 = 3.88 | 0.049* |
| ≤ 40 hours | 30 (34.9%) | 41 (50.0%) | - | - |
| > 40 hours | 56 (65.1%) | 41 (50.0%) | - | - |
When comparing groups, nurses working in public hospitals were more likely to be assigned to rotating shifts than those in private hospitals (76.7% vs. 61.0%, χ2 = 4.61, p = 0.032). They were also more likely to work beyond 40 hours per week (65.1% vs. 50.0%, χ2 = 3.88, p = 0.049). Regarding unit placement, a larger proportion of public hospital nurses worked in emergency departments (40.7%), whereas private hospital nurses were more frequently assigned to ICUs (35.4%). This distribution differed significantly between the two groups (χ2 = 6.24, p = 0.044).
No meaningful differences were observed in terms of gender (χ2 = 0.12, p = 0.73) or marital status (χ2 = 0.35, p = 0.56). Although nurses in public hospitals were slightly older on average (32.1 ± 6.6 years) compared to those in private hospitals (31.0 ± 6.2 years), the difference was not statistically significant (t = 1.09, p = 0.28).
Overall, the mean burnout score (MBI total) was 51.3 ± 10.7, indicating moderate levels of burnout among participants. Nurses in private hospitals reported higher burnout scores (53.1 ± 11.0) than those in public hospitals (49.6 ± 10.2), and this difference reached statistical significance (t = -2.08, p = 0.039) (Table 2).
| Variable |
Public (n=86) Mean ± SD |
Private (n=82) Mean ± SD |
Test (t) | p-value |
|---|---|---|---|---|
| Burnout (MBI total) | 49.6 ± 10.2 | 53.1 ± 11.0 | -2.08 | 0.039* |
| Emotional exhaustion | 18.4 ± 5.6 | 20.1 ± 6.0 | -1.93 | 0.046* |
| Depersonalization | 11.2 ± 4.1 | 12.5 ± 4.3 | -1.89 | 0.061 |
| Personal accomplishment | 19.9 ± 5.0 | 18.6 ± 5.3 | 1.97 | 0.050 |
| Work-Life Balance | 3.41 ± 0.62 | 3.18 ± 0.65 | 2.29 | 0.023* |
| Leisure Engagement Index | 3.52 ± 0.71 | 3.29 ± 0.75 | 1.79 | 0.075 |
Looking at specific dimensions, emotional exhaustion was significantly greater among nurses in private hospitals (20.1 ± 6.0) compared to those in public hospitals (18.4 ± 5.6; t = -1.93, p = 0.046). Depersonalization followed a similar pattern but did not reach statistical significance (t = -1.89, p = 0.061). In contrast, public hospital nurses reported slightly higher personal accomplishment scores (19.9 ± 5.0 vs. 18.6 ± 5.3; t = 1.97, p = 0.050), suggesting a relatively stronger sense of professional fulfillment.
Work-life balance was also higher among public hospital nurses (3.41 ± 0.62) than among those in private hospitals (3.18 ± 0.65), with the difference being statistically significant (t = 2.29, p = 0.023). Although leisure engagement scores were somewhat higher in the public group (3.52 ± 0.71 vs. 3.29 ± 0.75), this difference did not reach statistical significance (t = 1.79, p = 0.075).
Correlation analyses revealed consistent patterns across both hospital types (Table 3). In public hospitals, burnout showed a moderate negative association with work-life balance (r = −.44, p < .001) and leisure engagement (r = −.31, p = .004), while it was positively related to workload (r = .38, p < .001). Work-life balance was positively associated with leisure engagement (r = .27, p = .011) and negatively associated with workload (r = −.35, p < .001).
| Variable | Burnout | Leisure Engagement | Work-Life Balance | Workload |
|---|---|---|---|---|
| Public Hospitals (n = 86) | - | - | - | - |
| Burnout | 1 | - | - | - |
| Leisure engagement | −.31** | 1 | - | - |
| Work-life balance | −.44*** | .27* | 1 | - |
| Workload | .38*** | −.19 | −.35*** | 1 |
| Private Hospitals (n = 82) | - | - | - | - |
| Burnout | 1 | - | - | - |
| Leisure engagement | −.36** | 1 | - | - |
| Work-life balance | −.49*** | .32** | 1 | - |
| Workload | .44*** | −.24* | −.41*** | 1 |
In private hospitals, these relationships appeared slightly stronger. Burnout had a stronger negative correlation with work-life balance (r = −.49, p < .001) and was also inversely associated with leisure engagement (r = −.36, p = .001). At the same time, the positive relationship between burnout and workload was more pronounced (r = .44, p < .001), indicating that workload pressures may play a larger role in burnout among nurses in private settings. Leisure engagement and work-life balance were positively correlated (r = .32, p = .003), and both variables were negatively related to workload.
Multivariable regression analyses further confirmed these findings (Table 4). Leisure engagement was associated with lower burnout in both public (B = −1.74, 95% CI [−3.20, −0.28], p = .021) and private hospitals (B = −2.96, 95% CI [−4.58, −1.34], p = .001). Work-life balance demonstrated a stronger protective effect in private hospitals (B = −5.21, p < .001) compared to public hospitals (B = −3.89, p < .001).
| Predictor | Public Hospitals | Private Hospitals | ||||
|---|---|---|---|---|---|---|
| B (SE) | 95% CI | p | B (SE) | 95% CI | p | |
| Leisure engagement | −1.74 (0.74) | −3.20, −0.28 | .021 | −2.96 (0.83) | −4.58, −1.34 | .001 |
| Work-Life Balance | −3.89 (0.85) | −5.55, −2.23 | < .001 | −5.21 (0.92) | −7.01, −3.41 | < .001 |
| Leisure × WLB | −1.21 (0.59) | −2.37, −0.05 | .041 | −2.54 (0.76) | −4.03, −1.05 | .001 |
| Shift work (yes) | 3.12 (1.23) | 0.71, 5.53 | .012 | 4.68 (1.14) | 2.45, 6.91 | < .001 |
| Weekly hours >40 | 2.14 (1.02) | 0.15, 4.13 | .037 | 3.45 (1.15) | 1.19, 5.71 | .003 |
| Workload | 3.87 (0.76) | 2.38, 5.36 | < .001 | 4.96 (0.81) | 3.37, 6.55 | < .001 |
Importantly, the interaction between leisure engagement and work-life balance was statistically significant in both groups, with a larger effect observed in private hospitals (B = −2.54) than in public hospitals (B = −1.21). This suggests that WLB plays a more substantial buffering role in private hospital settings.
In addition, shift work, longer working hours, and higher workload were consistently linked to increased burnout across both groups. These effects were more pronounced among nurses in private hospitals, suggesting higher vulnerability in this setting.
Further analysis using simple slopes (Table 5) provided deeper insight into the moderating role of work-life balance. At low levels of WLB, leisure engagement was not significantly associated with burnout in either public (B = −0.62, p = .311) or private hospitals (B = −1.41, p = .082).
| WLB Level | Public Hospitals | Private Hospitals | ||||
|---|---|---|---|---|---|---|
| B (SE) | 95% CI | p | B (SE) | 95% CI | p | |
| Low (−1 SD) | −0.62 (0.61) | −1.82, 0.58 | .311 | −1.41 (0.80) | −2.99, 0.17 | .082 |
| Mean | −1.74 (0.74) | −3.20, −0.28 | .021 | −2.96 (0.83) | −4.58, −1.34 | .001 |
| High (+1 SD) | −2.89 (0.69) | −4.24, −1.54 | < .001 | −4.38 (0.77) | −5.89, −2.87 | < .001 |
At average levels of WLB, leisure engagement was significantly associated with lower burnout in both public (B = −1.74, p = .021) and private hospitals (B = −2.96, p = .001).
At high levels of WLB, the protective effect of leisure engagement became much stronger, particularly in private hospitals (B = −4.38, 95% CI [−5.89, −2.87], p < .001). This indicates that when nurses experience better balance between work and personal life, the stress-reducing benefits of leisure activities become more pronounced.
Overall, the moderating effect of work-life balance was evident in both hospital types but differed in magnitude (Table 6). In public hospitals, the interaction effect was relatively modest (B = −1.21, 95% CI [−2.37, −0.05], p = .041), whereas in private hospitals it was notably stronger (B = −2.54, 95% CI [−4.03, −1.05], p = .001). This pattern suggests that organizational context plays an important role in shaping how leisure activities and work-life balance interact to influence burnout.
| Group | Leisure × WLB B (SE) | 95% CI | p |
|---|---|---|---|
| Public hospitals | −1.21 (0.59) | −2.37, −0.05 | .041 |
| Private hospitals | −2.54 (0.76) | −4.03, −1.05 | .001 |
4. DISCUSSION
Burnout among nurses continues to pose a serious challenge within healthcare systems, affecting not only workforce stability but also patient safety and quality of care. A substantial body of evidence has consistently linked burnout to increased clinical errors, lower patient satisfaction, and declining care standards, highlighting the urgency of identifying effective protective mechanisms in clinical settings [1, 9]. In the post-pandemic period, this issue has become even more pronounced, with nurses reporting greater emotional strain and reduced job satisfaction compared to other healthcare professionals [3]. Against this backdrop, the present study offers additional insight by showing that the protective effect of leisure-based activities is not uniform, but instead depends on nurses’ Work-Life Balance (WLB) and varies across hospital contexts.
The findings can be further interpreted through the Job Demands-Resources (JD-R) model and Conservation of Resources (COR) theory. According to the JD-R model, burnout develops when job demands continuously exceed available resources. In nursing environments characterized by high workload, shift work, and emotional demands, work-life balance functions as an important personal resource that helps nurses regulate energy expenditure and psychological recovery. The significant interaction between leisure engagement and WLB suggests that leisure activities are more beneficial when nurses possess sufficient resources to disengage from work demands.
From the COR perspective, individuals attempt to acquire, preserve, and restore valuable resources. Leisure activities may represent a recovery resource by restoring emotional and psychological capacity; however, when nurses experience severe work-life imbalance, limited time and persistent fatigue may prevent them from fully benefiting from leisure experiences. Therefore, WLB may serve as an enabling condition that determines whether leisure resources can effectively reduce burnout.
Work-life balance has long been recognized as a key factor influencing nurses’ well-being and job engagement. When nurses are able to maintain a healthy balance between professional and personal roles, they tend to report higher levels of positive emotions, job satisfaction, and engagement. In contrast, ongoing conflict between work and personal life is associated with psychological distress and tension between family and professional responsibilities [5, 6]. A recent socio-ecological review further emphasizes that WLB is shaped by multiple layers, including institutional policies, staffing systems, and broader healthcare structures [7].
The findings of this study add to the existing literature by suggesting that WLB plays a more complex role than previously understood. Rather than acting solely as a direct predictor of burnout, WLB also influences how effectively nurses can benefit from leisure-related recovery. This is consistent with recovery theory, which highlights the importance of sufficient time, autonomy, and mental detachment from work in enabling true psychological restoration [17]. When WLB is compromised, leisure activities may be overshadowed by fatigue, limited time, and lingering work-related stress, thereby reducing their potential to support recovery.
Leisure-based activities-such as exercise, social interaction, and engaging hobbies-are increasingly acknowledged as valuable strategies for stress relief among healthcare professionals. Previous research has shown that structured leisure interventions can alleviate stress, anxiety, and depressive symptoms in nurses [8]. Similarly, regular physical activity has been associated with lower burnout levels through improved recovery experiences [9]. In addition, the concept of “leisure crafting,” in which individuals actively shape meaningful leisure experiences, has been identified as a predictor of lower burnout using advanced analytical methods.
The current findings reinforce these perspectives but also highlight an important nuance: leisure engagement appears to be most effective when supported by adequate WLB. In other words, engaging in leisure activities alone may not be sufficient in highly demanding work environments. From a management standpoint, this suggests that individual-level wellness initiatives should be complemented by organizational efforts that promote a healthier balance between work and personal life.
Hospital type also emerged as an important contextual factor influencing the relationship between leisure engagement and burnout. Previous studies have demonstrated differences between public and private hospitals in terms of workload, organizational resources, and burnout levels, with nurses in private settings often experiencing higher emotional exhaustion and depersonalization [10, 11]. These differences may stem from variations in staffing structures, performance expectations, employment conditions, and management practices.
In this study, the moderating role of WLB was more pronounced in private hospitals, suggesting that nurses in these environments may rely more heavily on WLB to benefit from leisure activities. From the perspective of the Job Demands-Resources framework, this finding is understandable: when job demands are high and organizational support is limited, personal recovery strategies require stronger enabling conditions to be effective [12]. This underscores the need for context-sensitive approaches to workforce well-being, rather than applying a one-size-fits-all strategy across different healthcare sectors.
Consistent with prior research, occupational demands such as shift work, long working hours, and heavy workload were strongly associated with higher burnout levels [12]. Rotating shifts can disrupt circadian rhythms and reduce sleep quality, while excessive workload limits both the time and energy available for recovery. These findings highlight that addressing burnout cannot rely solely on encouraging individual coping strategies. Instead, structural interventions-such as improving staffing levels, optimizing workload distribution, and implementing more supportive scheduling systems-remain essential. Without such systemic changes, the long-term effectiveness of wellness programs may be limited.
5. CLINICAL AND NURSING MANAGEMENT IMPLICATIONS
The results of this study suggest that burnout prevention requires a balanced and integrated approach. First, healthcare institutions should strengthen policies that support work-life balance, such as implementing more predictable schedules, limiting excessive overtime, ensuring adequate staffing, and allowing greater flexibility in shift arrangements. These measures create the foundation necessary for meaningful recovery outside of work.
Second, leisure-oriented wellness programs-including physical activity initiatives, social engagement opportunities, and structured recreational activities-should be incorporated into broader workforce strategies rather than treated as standalone interventions. Evidence indicates that such programs are most effective when supported by favorable working conditions [8, 9].
Third, targeted interventions may be particularly important in private hospital settings, where nurses appear more vulnerable to burnout when WLB is insufficient. Addressing factors such as performance pressure, staffing stability, and integration between work and personal life may yield greater benefits than generic well-being programs.
Finally, given the well-established connection between nurse burnout and patient safety, efforts to improve workforce well-being should also be viewed as investments in care quality and safety outcomes [1, 2].
6. STUDY LIMITATIONS
Several limitations should be considered when interpreting these findings. The cross-sectional nature of the study limits the ability to establish causal relationships, and the associations observed may be bidirectional. The use of self-reported data may also introduce response bias and common-method variance.
Additionally, because burnout, work-life balance, and leisure engagement were assessed using self-reported questionnaires, social desirability bias may have influenced responses. Participants may have underestimated burnout symptoms or overreported positive lifestyle behaviors. Furthermore, subgroup interaction analyses by hospital type should be interpreted cautiously because the sample size within each group may have limited statistical power for detecting smaller interaction effects. Future studies with larger multicenter samples are recommended to confirm these moderation effects.
Although important demographic and occupational variables were controlled, other potentially influential factors-such as leadership style, staffing ratios, and compensation systems-were not included in the analysis. Additionally, the study was conducted within a specific regional context, which may limit the generalizability of the findings to other settings. Future research using longitudinal designs and multi-center samples is needed to better understand causal mechanisms and contextual influences.
CONCLUSION
This study highlights that engaging in leisure-based activities can help reduce burnout among nurses, but its effectiveness depends largely on work-life balance and organizational context. Work-life balance plays a key moderating role by enabling leisure activities to function as meaningful recovery strategies. This effect is particularly evident in private hospital settings, where occupational demands may be higher.
Therefore, efforts to prevent burnout should not focus solely on individual behaviors but should combine organizational policies that support work-life balance with opportunities for restorative leisure. Such integrated strategies have the potential to enhance nurse well-being, strengthen workforce sustainability, and ultimately improve the quality and safety of patient care.
AUTHORS’ CONTRIBUTIONS
All authors contributed substantially to the conception, design, analysis, and interpretation of the study. R.F.L., D.H.C.: Conceptualization; R.F.L., G.A., A.A.P.: Methodology; G.A., A.A.P.: Data Collection; R.F.L: Formal Analysis; R.F.L.: Writing - Original Draft; E.F.L., D.H.C.: Writing - Review and Editing; D.H.C.: Supervision. All authors reviewed and approved the final manuscript.
LIST OF ABBREVIATIONS
| WLB | = Work-Life Balance |
| ICUs | = Intensive Care Units |
| MBI-HSS | = Maslach Burnout Inventory-Human Services Survey |
| LEI | = Leisure Engagement Index |
| EFA | = Exploratory Factor Analysis |
| VIF | = Variance Inflation Factor |
| CFA | = Confirmatory Factor Analysis |
| CFI | = Comparative Fit Index |
| TLI | = Tucker-Lewis Index |
| RMSEA | = Root Mean Square Error of Approximation |
| SRMR | = Standardized Root Mean Square Residual |
| MICE | = Multiple Imputation using Chained Equation |
| CIs | = Confidence Intervals |
| JD-R | = Job Demands-Resources |
| COR | = Conservation of Resources |
ETHICS APPROVAL AND CONSENT TO PARTICIPATE
This study received ethical approval from Universitas Hang Tuah (Approval No.: 008/KEPK/UHTP/XI/2025).
HUMAN AND ANIMAL RIGHTS
All procedures involving human participants were conducted in accordance with the ethical standards of the committee responsible for human experimentation (institutional and national), and with the Helsinki Declaration of 1975, as revised in 2013.
DATA AVAILABILITY STATEMENT
The datasets generated and analyzed during the current study are not publicly available due to ethical restrictions and participant confidentiality but are available from the corresponding author upon reasonable request and approval from the institutional ethics committee.
ACKNOWLEDGEMENTS
The authors sincerely thank the participating hospitals and nursing staff for their cooperation and valuable contributions to this research.

