All published articles of this journal are available on ScienceDirect.

Knowledge of Delirium among ICU Nurses in Saudi Arabia: A Cross-Sectional Assessment
 iD
Authors Info & Affiliations
Abstract
Introduction
Delirium is a common yet frequently underrecognized complication in Intensive Care Units (ICUs), where nurses play a key role in early detection and intervention. This study assessed ICU nurses’ knowledge of delirium across five domains and examined associated demographic and professional factors.
Methods
A cross-sectional study was conducted between January and February 2025 among the entire eligible population of ICU nurses (n = 123) across four adult ICUs in Saudi Arabia. Knowledge was assessed using an adapted 35-item Delirium Knowledge Questionnaire, with items grouped into five reporting domains. Descriptive statistics, independent-samples t-tests, and one-way analysis of variance were used.
Results
The mean total knowledge score was 25.4 ± 4.2 (72.6%). Clinical Features had the highest mean percentage score (76.7%), followed by General Knowledge (75.7%), whereas Delirium Management had the lowest score (60.0%). Prior delirium training was associated with higher total knowledge scores (MD = 4.10, 95% CI: 2.32–5.88; Cohen’s d = 0.93; p < 0.001). ICU experience was also associated with total knowledge scores (p = 0.032; η2 = 0.086).
Discussion
Overall, knowledge of delirium was moderate to high, whereas management-related knowledge was comparatively lower. The findings identify management as a priority area for educational reinforcement. Associations involving ICU experience should be interpreted with caution because some subgroups were small.
Conclusion
ICU nurses demonstrated moderate-to-high knowledge of delirium, with a notable gap in management-related content. Prior training and ICU experience were associated with higher knowledge scores, supporting the need for targeted delirium education and standardized assessment practices.
1. INTRODUCTION
Delirium is an acute, fluctuating disturbance of consciousness, cognition, and attention, commonly observed among critically ill patients admitted to Intensive Care Units (ICUs). Globally, estimates indicate that it affects between 30% and 80% of ICU patients, particularly those who are mechanically ventilated or recovering from surgery, making its prevention and management a critical priority in ICU settings [1-3]. Beyond its high incidence, delirium is a strong predictor of poor clinical trajectories, including a threefold increase in mortality and long-term ICU-acquired cognitive impairment [4]. Despite its status as a quality-of-care indicator, recognition remains suboptimal. In particular, the hypoactive subtype, characterized by withdrawal and lethargy, is often missed, even though it comes with the highest risk of mortality due to its silent clinical presentation [3-5].
The etiology of delirium is multifactorial, involving predisposing factors such as chronic illness, cognitive impairment, and advanced age, together with precipitating triggers like infection, exposure to sedatives or other psychoactive drugs, electrolyte imbalance, and environmental stressors in the ICU [2, 4, 5]. This risk is further increased by limited family engagement, sensory deprivation, physical restraints, and sleep disruption [3, 5]. Diagnosing delirium is particularly challenging due to its fluctuating nature and overlap with other neurocognitive disorders, especially among mechanically ventilated ICU patients and those with hypoactive delirium. Historically, pharmacological interventions such as antipsychotics have been used for symptom control, but recent evidence suggests limited benefit and potential adverse effects, especially when used routinely [3, 4, 6]. Consequently, international guidelines increasingly emphasize non-pharmacological approaches as the foundation for delirium prevention and care [7, 8]. These include engaging family members in care, effective communication, minimizing sensory deprivation, cognitive stimulation, early mobilization, and optimizing sleep-wake cycles [1, 9-12].
To prevent complications, early detection of delirium is essential. Current ICU guidance emphasizes delirium as a core ICU outcome. It supports standardized monitoring with validated tools, alongside prevention/management strategies, thereby promoting its integration into routine ICU practice rather than treating assessment as optional [9]. Tools like the Confusion Assessment Method for the ICU (CAM-ICU) and the Intensive Care Delirium Screening Checklist (ICDSC) are widely used to identify changes in consciousness or attention [3, 4, 6]. These tools rely on monitoring changes in mental status, attention, and consciousness, enabling healthcare providers to identify delirium early and initiate appropriate interventions. Nevertheless, their use remains inconsistent, with many ICU nurses reporting limited confidence in their effective application [11, 13-15].
ICU nurses play a central role in delirium care. Their continuous bedside presence enables early detection of cognitive changes and timely implementation of preventive measures [12, 16]. However, studies consistently show that ICU nurses have limited knowledge of delirium, particularly regarding the use of validated screening tools, recognition of hypoactive presentations, and identification of risk factors [17]. Similarly, Grover et al. [14] reported that most nurses had not received formal training in delirium and rarely prioritized its assessment. In Poland, Lange et al. [18] found that fewer than a fifth of ICU nurses routinely screened for delirium, citing a lack of institutional protocols and insufficient training as key barriers. A study in India concluded that although slightly more than three-fifths of nurses had average knowledge, few could demonstrate a robust understanding of non-pharmacological management [19]. These findings underscore the need for targeted education, as studies have shown that training can improve nurses’ ability to recognize and manage delirium, particularly hypoactive delirium, and to use standardized assessment tools effectively [20-23].
Previous Saudi research has assessed nurses’ knowledge of delirium across mixed acute-care settings [15]. However, evidence from Saudi Arabia remains limited regarding ICU-specific, domain-level assessments of the knowledge required for contemporary delirium care. Therefore, this study aimed to assess delirium knowledge among ICU nurses across five clinically relevant domains: general knowledge, clinical features, etiology and risk factors, management, and non-pharmacological interventions, central to early recognition and effective bedside prevention. By identifying specific domain-level gaps, this work identifies where education fails to translate into ICU expertise and provides a practical baseline for targeted, evidence-based ICU educational interventions in settings with a substantial burden of delirium.
2. MATERIALS AND METHODS
2.1. Research Design
This study employed a cross-sectional, exploratory design to assess ICU nurses’ knowledge of delirium. A cross-sectional design was appropriate for capturing a snapshot of knowledge within the active ICU nursing workforce at a single point in time [24]. The exploratory component enabled domain-level profiling across five key areas: general understanding, clinical features, risk factors, management, and non-pharmacological strategies. This design also enabled the examination of associations between participants’ demographic and professional characteristics, such as ICU years of experience and previous training, and their overall delirium knowledge scores.
2.2. Setting and Samples
The study employed a total population sampling approach, targeting the full roster of ICU nurses (N = 143) working across the four adult intensive care units that represent all adult ICU services in Hail City, Saudi Arabia. This approach was selected because the eligible ICU nursing population was relatively small and accessible, allowing comprehensive assessment without selecting a subsample. Eligibility screening was conducted before recruitment. Based on predefined eligibility criteria, 20 nurses were excluded: those with less than 6 months of ICU clinical experience or those on extended leave during the data collection period. The six-month criterion was intended to include nurses who had completed their initial orientation period and gained sufficient exposure to routine ICU practice, while nurses on extended leave were excluded because they were not actively engaged in clinical care during the study period. Consequently, 123 nurses were eligible for inclusion, and all completed the questionnaire, resulting in 100% participation among the eligible population rather than the full roster of 143 nurses. A participant flow diagram illustrating eligibility screening, exclusions, recruitment, and inclusion in the final analysis is presented in Fig. (1). This near-census of the accessible workforce strengthens the sample's representativeness; however, the exclusion criteria may limit the applicability of the findings to newly appointed nurses and those temporarily absent from clinical practice.
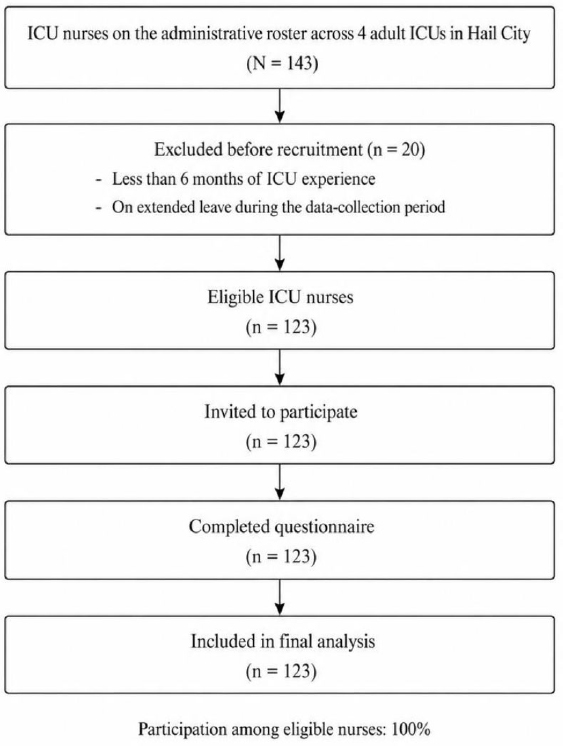
Participant flow through eligibility screening, recruitment, and final analysis.
2.3. Measurement and Data Collection
Data were collected electronically between January and February 2025 using a self-administered questionnaire designed to assess ICU nurses’ knowledge of delirium. Demographic and professional data were also collected, including age, gender, educational level, job position, years of ICU experience, hospital site, and previous training in delirium management. An adapted version of the Delirium Knowledge Questionnaire developed by Detroyer et al. [25] was used to assess delirium knowledge. The original 35-item true/false instrument was adapted from Hare et al. [26] and structured to assess three core domains: delirium presentation, symptoms, and outcomes; causes and risk factors; and prevention and management strategies. A panel of five experts evaluated the instrument's validity, including senior ICU clinicians and nursing academics with more than 10 years of experience in the Saudi healthcare sector. In addition to assessing item relevance and clarity, the panel examined the instrument’s conceptual organization. It supported the regrouping of the 35 items into five conceptually relevant domains for analytical purposes: General Knowledge (items 2, 3, 4, 7, and 23), Clinical Features (items 1, 5, 6, 8, 9, and 10), Etiology and Risk Factors (items 11–21), Delirium Management (items 22, 25, and 29), and Non-Pharmacological Interventions (items 24, 26–28, and 30–35). The purpose of this revised classification was to improve the interpretability of the findings by clearly distinguishing foundational knowledge, symptom recognition, risk identification, management principles, and supportive care strategies. This classification was used only for domain-level analysis and did not represent a modification or psychometric revalidation of the original instrument. The original item content and total scoring range were retained. Following the expert panel’s recommendation, an “I don’t know” response option was added. This modification was designed to distinguish uncertainty from affirmative or negative responses and to reduce forced guessing, thereby improving the accuracy of measurements of nurses' true knowledge levels [27]. Responses were scored as follows: 1 for a correct answer and 0 for an incorrect or “I don’t know” response, producing a total score ranging from 0 to 35. Because “I don’t know” responses received the same score as incorrect responses, the total score calculation and maximum possible score remained unchanged. However, the modified response format may limit direct comparability with studies that used the original binary response format.
Content validity was established by a panel of five experts, who confirmed the technical relevance of the English- language items to the local ICU setting, yielding a scale-level content validity index based on the average method (S-CVI/Ave) of 0.96. The instrument’s face validity was further confirmed by a pilot test (n = 10), who reported no language or clarity concerns. The instrument’s face validity was further assessed through a pilot test involving 10 nurses, who reported no language or clarity concerns. Pilot participants were excluded from the final study sample. The final tool attained a Cronbach’s alpha of 0.944, demonstrating high reliability. The survey was administered in English, which is the official language used for healthcare delivery and professional communication in the Saudi Arabian hospital system. The questionnaire was distributed to all eligible ICU nurses through the hospital’s official communication channels. Participants received an information sheet, electronic consent form, and survey link, with weekly reminders sent throughout the data-collection period. Only fully completed questionnaires were included in the analysis, and no duplicate or incomplete responses were identified.
2.4. Data Analysis
IBM SPSS Statistics version 29.0 was used for data analysis. Data were summarized using frequencies, percentages, means, and standard deviations to describe demographic characteristics and knowledge scores. Raw scores were converted to percentages to facilitate comparison across the five domains, which varied in the number of items. To ensure consistent scoring, 'I don’t know' responses were scored as incorrect (0). Independent-samples t-tests were used to compare mean knowledge scores across variables with two categories (gender and previous delirium training), whereas one-way Analysis of Variance (ANOVA) was used for variables with three or more categories (age, educational level, ICU experience, hospital site, and job position). Mean differences with 95% confidence intervals and Cohen’s d were reported for two-group comparisons. Eta-squared (η2) was reported as the effect size for ANOVA comparisons. Score distributions were inspected for substantial departures from normality, and homogeneity of variance was assessed using Levene’s test. Results are presented with test statistics, degrees of freedom, p-values, effect estimates, and effect sizes. All statistical tests were two-tailed, with significance set at p < 0.05.
3. RESULTS
3.1. Demographic and Professional Profile
Out of the 123 ICU nurses included in this study, 65.9% were males. Participants aged 20–29 years accounted for 62.6% of the sample. Most participants held a bachelor’s degree (82.1%), and 60.2% worked as staff nurses. Half of the participants (50.4%) had between one and five years of ICU experience. Only 26.8% had received prior delirium training, as shown in Table 1.
| Variable | Category | n (%) |
|---|---|---|
| Gender | Female | 42 (34.1%) |
| Male | 81 (65.9%) | |
| Age (years) | 20–29 years | 77 (62.6%) |
| 30–39 years | 43 (35.0%) | |
| 40–49 years | 3 (2.4%) | |
| Education | Bachelor’s degree | 101 (82.1%) |
| Postgraduate diploma | 16 (13.0%) | |
| Master’s degree | 5 (4.1%) | |
| Other | 1 (0.8%) | |
| Years of Experience | < 1 year | 10 (8.1%) |
| 1–5 years | 62 (50.4%) | |
| 5–10 years | 22 (17.9%) | |
| 10–15 years | 25 (20.3%) | |
| > 15 years | 4 (3.3%) | |
| Hospital Site | Hospital (1) | 37 (30.1%) |
| Hospital (2) | 51 (41.5%) | |
| Hospital (3) | 15 (12.2%) | |
| Hospital (4) | 20 (16.3%) | |
| Job Position | Staff nurse | 74 (60.2%) |
| Charge nurse | 33 (26.8%) | |
| Nursing supervisor | 12 (9.8%) | |
| Head nurse | 4 (3.3%) | |
| Received Previous Training on Delirium | Yes | 33 (26.8%) |
| No | 90 (73.2%) |
3.2. Factors Associated with Delirium Knowledge
As shown in Table 2, nurses who had received prior delirium training scored an average of 4.10 points higher than those who had not, t(121) = 4.56, p < 0.001, MD = 4.10, 95% CI: 2.32–5.88, Cohen’s d = 0.93. ICU experience was also significantly associated with total knowledge scores, F(4, 118) = 2.77, p = 0.032, η2 = 0.086. Gender, age, educational level, hospital site, and job position were not significantly associated with total knowledge scores.
| Variable | Category | n | Mean ± SD | Test Statistic | p-value | Effect Estimate (95% CI) and Effect Size |
|---|---|---|---|---|---|---|
| Gender | Female | 42 | 25.4 ± 4.2 | t(121) = 0.01 | 0.993 | MD = 0.00 (95% CI: -1.61 to 1.61); d = 0.00 |
| Male | 81 | 25.4 ± 4.3 | ||||
| Age (years) | 20-29 | 77 | 25.5 ± 4.2 | F (2, 120) = 0.49 | 0.614 | η²= 0.008 |
| 30-39 | 43 | 25.4 ± 4.4 | ||||
| 40-49 | 3 | 21.7 ± 5.1 | ||||
| Educational level | Bachelor's degree | 101 | 25.7 ± 4.1 | F(3, 119) = 0.96 | 0.411 | η² = 0.024 |
| Postgraduate diploma | 16 | 24.8 ± 4.4 | ||||
| Master's degree | 5 | 23.6 ± 4.8 | ||||
| Other | 1 | — | ||||
| ICU experience (years) | <1 | 10 | 26.0 ± 4.1 | F (4, 118) = 2.77 | 0.032 | η²= 0.086 |
| 1-5 | 62 | 25.2 ± 4.3 | ||||
| 5-10 | 22 | 26.4 ± 3.9 | ||||
| 10-15 | 25 | 25.1 ± 4.4 | ||||
| >15 | 4 | 21.4 ± 5.2 | ||||
| Hospital site | Hospital 1 | 37 | 26.2 ± 4.1 | F (3, 119) = 0.40 | 0.753 | η²= 0.010 |
| Hospital 2 | 51 | 24.8 ± 4.5 | ||||
| Hospital 3 | 15 | 25.1 ± 4.2 | ||||
| Hospital 4 | 20 | 26.0 ± 4.3 | ||||
| Job position | Staff nurse | 74 | 25.5 ± 4.3 | F (3, 119) = 0.27 | 0.849 | η²= 0.007 |
| Charge nurse | 33 | 24.7 ± 4.4 | ||||
| Nursing supervisor | 12 | 26.0 ± 4.1 | ||||
| Head nurse | 4 | 25.9 ± 3.9 | ||||
| Previous delirium training | Yes | 33 | 28.4 ± 4.2 | t (121) = 4.56 | <0.001 | MD = 4.10 (95% CI: 2.32 to 5.88); d = 0.93 |
| No | 90 | 24.3 ± 4.5 |
3.3. Domain-Specific Knowledge Levels
Participants' performance across the five delirium knowledge domains is presented in Table 3. The mean total knowledge score was 25.4 ± 4.2, corresponding to an overall mean percentage score of 72.6%. The highest mean percentage score was observed in the Clinical Features domain (76.7%), followed by the General Knowledge domain (75.7%) and the Non-Pharmacological Interventions domain (75.6%). In contrast, the lowest mean percentage score was recorded in the Delirium Management domain (60.0%).
| Knowledge Domain | No. of Items | Mean ± SD | Mean Percentage Score |
|---|---|---|---|
| 1. General Knowledge on Delirium | 5 | 3.8 ± 1.4 | 75.7% |
| 2. Knowledge about Clinical Features | 6 | 4.6 ± 0.7 | 76.7% |
| 3. Knowledge about Etiology and Risk Factors | 11 | 7.9 ± 1.8 | 72.0% |
| 4. Knowledge about Delirium Management | 3 | 1.8 ± 0.9 | 60.0% |
| 5. Knowledge about Non-Pharmacological Interventions | 10 | 7.6 ± 1.5 | 75.6% |
| Total Knowledge Score | 35 | 25.4 ± 4.2 | 72.6% |
4. DISCUSSION
This study aimed to evaluate nurses' overall knowledge of delirium and identify demographic and professional associations, using domain-level analysis to identify specific knowledge gaps. The findings suggest that nurses had relatively strong foundational knowledge, alongside lower scores in delirium management. Prior delirium training and ICU experience were significantly associated with total knowledge scores. In contrast, no significant associations were found between knowledge scores and demographic characteristics such as gender and age.
The present study identified a relatively high level of delirium knowledge among ICU nurses, evidenced by a mean total score of 25.4 ± 4.2 (72.6%). This level was higher than the average or intermediate levels reported in several previous studies. However, direct comparisons across studies should be interpreted with caution due to differences in measurement instruments, scoring systems, participant populations, and clinical settings. For instance, using the same Delirium Knowledge Questionnaire framework, Mathew et al. [19] observed that 61.6% of ICU nurses had only average knowledge, highlighting an urgent need for reinforced education on prevention and treatment. In the same vein, Xing et al. [28] found that more than half of their ICU cohort performed at an intermediate level, with “excellent” ratings remaining statistically rare. This knowledge deficiency extends beyond the ICU; Papaioannou et al. [29] reported a correct response rate of only 42.2% among general ward nurses regarding delirium definitions and identification methods. Within Saudi Arabia, Almoliky et al. [15] reported that only 7.3% of acute care nurses achieved a good level of knowledge, whereas 66.1% demonstrated poor overall knowledge. In addition, 78.2% had inadequate knowledge of delirium assessment, indicating a substantial gap in early recognition and systematic screening.
Although these local findings contrast with the present results, which indicated relatively high overall knowledge, domain-level analysis identified important areas of weakness. Most notably, the mean percentage score for Delirium Management (60.0%) was lower than the scores observed in the other knowledge domains. This finding may indicate that general understanding is stronger than knowledge of pharmacological and protocol-based management. The comparatively low management score is consistent with prior evidence of gaps in nurses’ knowledge of delirium prevention and management [10, 30], suggesting that although general concepts are grasped, the depth of clinical application remains insufficient for high-level critical care. Interestingly, this cohort demonstrated relatively strong knowledge of non-pharmacological management (75.6%), exceeding levels reported by Mathew et al. [19]. This finding also contrasts with that of Grover et al. [14], who reported that ICU nurses generally lacked awareness of non-pharmacological strategies. Given that only 26.8% of the current study sample had received previous delirium education, knowledge of interventions such as patient orientation and sensory stimulation may have been acquired through routine clinical exposure rather than structured education. However, this study did not assess actual bedside practice or the source of participants’ knowledge.
Previous delirium training was associated with higher total knowledge scores, with a large effect size (p < 0.001; Cohen’s d = 0.93). Despite the relatively high mean knowledge score of 73.2%, 73.2% of participants reported not having received formal delirium education, consistent with findings among Saudi acute-care nurses [15]. This pattern may suggest that informal clinical exposure could contribute to baseline knowledge; however, the study did not examine other potential sources of knowledge, such as self-directed learning, informal bedside teaching, or institutional protocols. Therefore, the coexistence of relatively high knowledge scores and limited reported formal training should be interpreted cautiously. Nevertheless, the higher scores among nurses who had received training support the value of structured delirium education [16, 18, 19, 28]. Previous studies have similarly indicated that education should extend beyond definitions to include bedside application, subtype recognition, assessment, and management planning [10, 30].
A notable finding was the non-linear association between professional experience and knowledge of delirium. Nurses with less than one year of ICU experience had a higher mean knowledge score than those with more than 15 years of experience. While the small size of the most senior subgroup (n = 4; 3.3%) precludes definitive statistical generalization, this trend suggests a potential 'recency effect.' It could indicate that recent graduates may be more attuned to current evidence-based guidelines integrated into modern nursing curricula. In contrast, senior staff may experience 'knowledge decay' in the absence of structured refreshers. Nonetheless, no definitive conclusions regarding a 'recency effect' or 'knowledge decay' can be drawn; the trend remains strictly exploratory. This finding contrasts with Christensen [17], who reported no significant association between experience and knowledge and highlighted a critical need to re-evaluate ongoing competency development for senior ICU staff to prevent knowledge decay.
Gender, age, education level, and job title were not significantly associated with total knowledge scores. Although Almoliky et al. [15] reported higher knowledge of assessment methods among female nurses, the present findings align with those of Grover et al. [14]. These results suggest that knowledge differences in this sample were not clearly explained by the measured demographic and professional characteristics. However, they should not be interpreted as evidence that such differences are absent in the broader ICU nursing population. Nevertheless, unit-wide education may help establish a consistent baseline of delirium knowledge among ICU nurses.
5. IMPLICATIONS
Based on the lower scores observed in delirium management and the association between prior training and higher knowledge, healthcare institutions may consider strengthening competency-based delirium education and reinforcing the use of validated delirium screening tools [13, 20-23]. Implementation could be coordinated by ICU nursing leadership in collaboration with nursing education and quality and patient safety teams. Delirium education could be incorporated into ICU orientation and reinforced through periodic education, audit and feedback, and clinical reminders, particularly when audits identify gaps in screening or management [31, 32].
Evidence from previous implementation studies suggests that multifaceted approaches, including education, reminders, local champions, and audit and feedback, can improve adherence to delirium-care practices [32, 33]. Simulation- and case-based learning may further support knowledge of delirium and assessment skills [34, 35]. In addition, structured approaches such as the ABCDE/ABCDEF bundle have been associated with improved delirium-related outcomes in critically ill adults by standardizing daily ICU routines, promoting lighter goal-directed sedation, and integrating non-pharmacological strategies such as early mobilization, sensory optimization, reorientation, and sleep regulation [36]. These recommendations should be interpreted as evidence-informed practice considerations, as the present study assessed knowledge only and did not evaluate clinical performance, implementation outcomes, or patient outcomes.
6. LIMITATIONS
This study has several limitations. It assessed self-reported theoretical knowledge rather than bedside performance or patient outcomes, and the cross-sectional design precludes causal inference. The use of a self-administered questionnaire may also have introduced response bias. Conducting the study in adult ICUs within a single Saudi city limits the generalizability of the findings, while excluding nurses with less than six months of ICU experience and those on extended leave may have introduced selection bias. Regrouping the Delirium Knowledge Questionnaire items and adding an “I don’t know” response option may limit comparability with studies using the original format. Finally, the small subgroup of nurses with more than 15 years of experience means that findings involving this group should be interpreted as exploratory.
CONCLUSION
ICU nurses demonstrated relatively high overall knowledge of delirium, although knowledge was lower in the delirium management domain. Previous delirium training and years of ICU experience were significantly associated with total knowledge scores. These findings highlight areas that may benefit from targeted continuing education and further evaluation of delirium assessment and management practices. Because of the cross-sectional design and the small sample sizes in some experience subgroups, the observed associations should be interpreted with caution.
AUTHORS’ CONTRIBUTIONS
The authors confirm contribution to the paper as follows: N.M.A. and F.H.A.: Study conception and design; S.S.A., T.D.A., S.S.A.: Data collection; N.M.A., J.M.: Analysis and interpretation of results; N.M.A., A.S.A., M.K.A., and M.O.A., A.A.: Draft manuscript preparation. All authors reviewed the results, critically revised the manuscript, and approved the final version of the manuscript.
LIST OF ABBREVIATIONS
| ABCDE | = Awakening and Breathing Coordination, Delirium Monitoring/Management, and Early Exercise/Mobility |
| ABCDEF | = Assess, Prevent, and Manage Pain; Both Spontaneous Awakening and Breathing Trials; Choice of Analgesia and Sedation; Delirium Assessment, Prevention, and Management; Early Mobility and Exercise; Family Engagement and Empowerment |
| ANOVA | = Analysis of Variance |
| CAM-ICU | = Confusion Assessment Method for the Intensive Care Unit |
| CI | = Confidence Interval |
| DKQ | = Delirium Knowledge Questionnaire |
| ICDSC | = Intensive Care Delirium Screening Checklist |
| ICU | = Intensive Care Unit |
| MD | = Mean Difference |
| S-CVI/Ave | = Scale-Level Content Validity Index Based on the Average Method |
| SD | = Standard Deviation |
| SPSS | = Statistical Package for the Social Sciences |
ETHICS APPROVAL AND CONSENT TO PARTICIPATE
Ethical approval was granted by the Ethics Committee of the Hail Region in January 2025 (Approval No. 2025-40).
HUMAN AND ANIMAL RIGHTS
All procedures involving human participants were conducted in accordance with the ethical standards of the committee responsible for human experimentation (institutional and national), and with the Helsinki Declaration of 1975, as revised in 2013.
CONSENT FOR PUBLICATION
Participants were asked to review an informed consent form along with an information sheet outlining the study objectives, measures to ensure data confidentiality, and the estimated time required to complete the survey.
AVAILABILITY OF DATA AND MATERIALS
The datasets used and/or analyzed during the current study are available from the corresponding author on reasonable request.
ACKNOWLEDGEMENTS
We sincerely thank all participants for their invaluable contributions to this study.

